
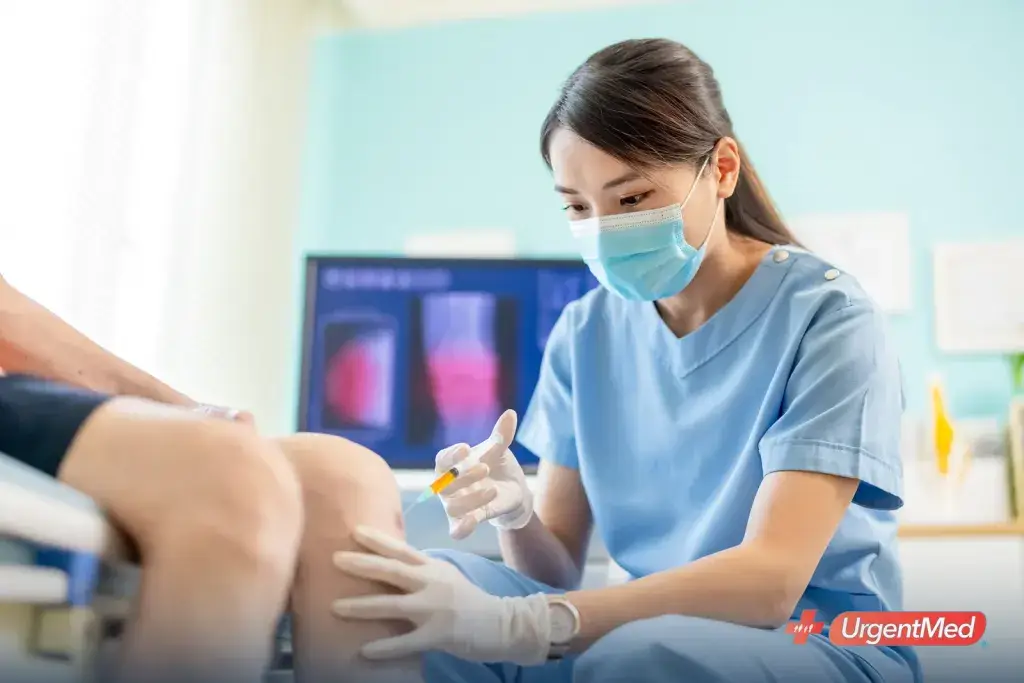
A painful knee, shoulder or hip, or a knot in the trapezius that will not release: a cortisone shot into the joint, or a trigger point injection, is given at the visit at both UrgentMed clinics, seven days a week, without a referral to a specialist first.
Cortisone shot — joint injections (intra-articular)
An intra-articular injection places a corticosteroid, with a local anesthetic, directly into an inflamed joint or bursa to reduce swelling and pain. The provider examines the joint, reviews any X-ray taken on site, and discusses whether an injection is the right next step or whether the problem needs orthopedic follow-up.
- Knee — osteoarthritis flares, bursitis, swelling after a strain.
- Shoulder — subacromial bursitis, rotator-cuff tendinopathy, frozen-shoulder pain.
- Hip — trochanteric bursitis (pain on the outside of the hip).
- Elbow and wrist — tennis and golfer’s elbow, de Quervain’s tenosynovitis.
- Foot and ankle — plantar fasciitis and ankle bursitis, when shockwave therapy or a splint is not the better option.
Steroid injections into the same joint are spaced out — typically no more than three or four a year — and the provider tells you what to expect in the first 48 hours and when to follow up.
Trigger point injections
A trigger point is a tight, tender band in a muscle that refers pain — commonly the upper trapezius and neck (tension headaches, “tech neck”), the lower back and gluteal muscles, and the shoulder blade. A trigger point injection places a small volume of local anesthetic, sometimes with a corticosteroid, into the knot to release it. Relief is often immediate; the provider pairs it with stretching and activity advice so it lasts.
Cortisone shot or trigger point injection — which fits which problem
The examination decides. Pain that comes from inside the joint — stiffness after rest, swelling, pain with weight-bearing — points to an intra-articular injection. Pain that comes from the muscle around it — a tender band that reproduces the ache when pressed, often with a headache or a stiff neck — points to a trigger point injection. Bursitis on the outside of the hip, the shoulder or the elbow is treated with an injection into the bursa, next to the sore tendon rather than into it, because repeated steroid weakens tendon tissue; the Achilles, patellar and biceps tendons are not injected at all.
Some problems are better served by something else. A suspected fracture or ligament tear needs imaging and splinting first. Tendon pain that keeps returning often does better with shockwave therapy and a rehabilitation plan than with another steroid. A hot, swollen joint with fever is not injected; it goes to the emergency room to rule out infection. OrthoInfo, the patient site of the American Academy of Orthopaedic Surgeons, explains how a cortisone shot works and why the number of shots a year is limited.
Injuries seen under workers’ compensation or a car accident PIP claim receive the same joint and trigger point injections at the visit, with medications dispensed on site and billed to the claim.
Other injections — a non-opioid pain shot for a migraine or acute back pain, an injectable antibiotic, a corticosteroid for a severe allergic reaction, vitamin B12 — are given at any walk-in visit and are described under injections given at the visit.
What to expect
- Examination, and X-ray on site when the joint needs imaging first.
- The injection takes a few minutes; the area is cleaned, numbed where appropriate and injected with a fine needle.
- You can usually go back to normal light activity the same day; the provider tells you what to avoid for 24–48 hours.
- Follow-up is scheduled when relief is partial or the problem needs a specialist, physical therapy or imaging.
Not sure an injection is what you need? General back, joint and muscle pain is evaluated at any walk-in visit, and the provider recommends an injection only when it is the right tool.
After the cortisone shot or injection
The anesthetic wears off within a few hours; the corticosteroid takes a day or two to work, and some people feel a brief flare of pain in the first one to two days before it settles. Ice, rest from the aggravating activity and the over-the-counter pain reliever the provider suggests cover that window. Relief from a joint injection commonly lasts several weeks. The point is to open a window for the stretching, activity change or physical therapy that keeps the problem from coming back, rather than to repeat the injection. Call the clinic for fever, spreading redness, or pain that increases rather than eases after any injection.
When to go to the emergency room instead
- A hot, red, swollen joint with fever — possible joint infection — or an injury with obvious deformity: go to the emergency room.
Walk in at either Broward clinic
Both clinics are open seven days a week — Davie at 5149 S University Drive (Renaissance Plaza, just south of Griffin Road) and Plantation at 10199 Cleary Boulevard, Suite 10. Both serve Davie, Plantation, Cooper City, Weston, Sunrise, Southwest Ranches, Pembroke Pines and the surrounding Broward County communities. Hours, maps and parking.
Insurance and self-pay
We accept most major insurance plans, workers’ compensation and Florida PIP auto claims, and quote self-pay pricing at the front desk before you are seen. Bring a photo ID and your insurance card.
Sources: MedlinePlus — Joint disorders